

Vitamin K Deficiency Bleeding: Why the Newborn Shot Matters and What Parents Should Know
America ı By Tyler Brooks
0 Comments

Key Takeaways
- Newborns naturally have low vitamin K reserves, putting them at risk of vitamin K deficiency bleeding (VKDB).
- The vitamin K1 shot is a nutrient injection recommended by the American Academy of Pediatrics since 1961.
- Oral vitamin K requires multiple doses and depends on proper absorption through the digestive system.
A single injection administered in the first hours of life has become a growing source of uncertainty for some new parents. The newborn vitamin K shot, a preventive dose of a nutrient rather than a vaccine, continues to spark debate despite decades of medical recommendations.
Its purpose is to prevent vitamin K deficiency bleeding (VKDB), a potentially life-threatening condition that can emerge weeks or even months after birth. The danger is particularly unsettling because a baby may appear perfectly healthy until bleeding begins. In some cases, the first warning comes from a hemorrhage inside the brain.
Every newborn begins life with low vitamin K reserves. The nutrient plays a critical role in blood clotting, and a baby's developing system starts with a limited supply. A single injection at birth provides the liver with vitamin K it can use during the vulnerable months when the body's natural supply remains insufficient.
The American Academy of Pediatrics (AAP) has recommended routine vitamin K administration for newborns since 1961. In the United States, the injection is a standard component of hospital newborn care, although it is not required by federal law and parents can decline it.
Several concerns about the shot continue to circulate. Some trace back to a 1990 study that raised questions about a possible childhood cancer link, a connection that subsequent research did not confirm. Other objections suggest breast milk provides enough vitamin K, that healthy babies born after uncomplicated deliveries do not need the injection, or that the dose is dangerously high.
Each concern deserves a closer look at the science behind newborn blood clotting.
The following 12 key points examine newborn vitamin K prophylaxis, why infants need the nutrient, how the injection works, the warning signs of bleeding and the evidence behind persistent myths. Questions about an individual baby's care should be discussed with a pediatrician.
1. The Vitamin K Shot Is a Nutrient Injection, Not a Vaccine
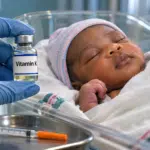
The newborn vitamin K injection contains vitamin K1, also known as phytonadione. It is administered into a baby's thigh muscle, usually during the first hours after birth.
The injection is designed to prevent vitamin K deficiency bleeding, a serious condition in which an infant's blood cannot clot properly.
The medication is delivered intramuscularly, meaning the needle places the vitamin into muscle tissue rather than beneath the skin or directly into a vein.
Despite recurring confusion, the vitamin K shot is not a vaccine or an immunization.
Vaccines introduce a germ, a harmless version of it or a component of it to the immune system. This process teaches the body to recognize and fight the pathogen if it encounters it in the future.
Vitamin K works through an entirely different mechanism.
It is a nutrient that the body uses directly in its own chemical processes. It does not train the immune system, trigger antibody production or create immune memory. It is also not included among the vaccines listed on the U.S. childhood immunization schedule.
The confusion largely stems from the timing and method of administration. A health care professional gives the vitamin K shot with a needle shortly after delivery. In many U.S. hospitals, the injection is administered during the same period as the first hepatitis B vaccine dose.
The two procedures may look similar, but their contents and purposes are fundamentally different.
In the United States, vitamin K administration is routine hospital newborn care. However, routine does not mean legally mandatory. No federal law requires the injection, and parents retain the right to refuse it.
Families with concerns can discuss the injection with a pediatrician before delivery, including how the family's medical history and pregnancy circumstances may affect the baby's care.
2. Why Newborns Begin Life With Low Vitamin K
Babies are born with limited vitamin K because only small amounts of the nutrient cross the placenta during pregnancy.
After birth, the two other sources that help supply vitamin K to older children and adults — intestinal bacteria and food — are not yet providing substantial amounts.
The Placenta Transfers Only Small Quantities
The placenta transports many nutrients from mother to fetus, but vitamin K is not transferred in large amounts.
Consequently, newborns arrive with limited reserves of the vitamin.
Vitamin K is fat-soluble, and the liver serves as its primary storage site. In newborns, those reserves are small and cannot sustain the body for long without additional vitamin K.
The Newborn Gut Has Not Yet Developed Its Bacterial Supply
In older children and adults, intestinal bacteria produce vitamin K2, also known as menaquinone.
A newborn's digestive tract has not yet been populated by these bacteria. Colonization begins at birth and develops over the following weeks and months.
That means the internal supply of vitamin K is not readily available during the earliest days of life.
Breast Milk Contains Relatively Little Vitamin K
Feeding creates another challenge.
Breast milk contains relatively low amounts of vitamin K. Babies who receive only breast milk therefore consume limited quantities of the nutrient each day, making it difficult to build adequate reserves quickly.
Infant formula differs because manufacturers supplement it with vitamin K. Formula-fed babies generally receive more of the vitamin through feeding than exclusively breastfed infants.
However, formula does not change the baby's starting point. Both formula-fed and breastfed infants are born with limited vitamin K reserves. Supplemented formula begins contributing to the baby's supply only after feeding starts.
The form of vitamin K found in leafy green vegetables is vitamin K1, or phylloquinone. The synthetic form used in the newborn injection is phytonadione.
Administering vitamin K shortly after birth helps bridge the gap until intestinal bacteria and regular feeding can provide more of the nutrient.
3. Vitamin K Is Essential for Blood Clotting
The liver requires vitamin K to produce four functional blood-clotting proteins: factors II, VII, IX and X.
Without sufficient vitamin K, these proteins cannot function properly, leaving the blood less capable of forming clots.
Blood clotting depends on a chain reaction involving several proteins. When an injury occurs, each protein activates the next, creating a cascade that eventually produces a stable clot.
Factor II, also known as prothrombin, plays a crucial role near the end of this process. Once activated, it becomes thrombin, an enzyme that converts fibrinogen into fibrin strands.
Those strands form the structure that holds a blood clot together.
How Vitamin K Activates Clotting Proteins
Vitamin K works during the final stages of manufacturing these proteins.
The liver produces the basic protein chains for factors II, VII, IX and X. An enzyme called gamma-glutamyl carboxylase then modifies specific glutamic acid units on each protein.
Vitamin K acts as a cofactor that the enzyme needs to complete this chemical process.
The modification allows the finished proteins to bind calcium. That calcium-binding ability helps them attach to the surfaces of platelets and damaged cells, where clotting takes place.
Without this step, the proteins may still circulate through the bloodstream, but they cannot properly anchor themselves where they are needed.
The consequences can be detected through a standard blood test.
When vitamin K levels are too low, the prothrombin time — a measure of how long blood takes to clot — becomes prolonged. Once vitamin K is supplied, the liver can resume producing functional clotting factors.
Vitamin K also supports proteins C and S, which help regulate the clotting process. Its role is not simply to make blood thicker; it helps the entire clotting system function correctly.
The Discovery of Vitamin K
Danish biochemist Henrik Dam identified vitamin K during research in the 1920s and 1930s.
His discovery began with observations of bleeding in chickens fed a fat-free diet.
The letter "K" comes from the German word "Koagulation," meaning coagulation.
For newborns, the underlying chemistry explains the danger. Even when the liver itself is healthy, a baby with insufficient vitamin K cannot produce enough functional clotting factors.
4. Vitamin K Deficiency Bleeding Has Three Forms
Vitamin K deficiency bleeding, or VKDB, is classified into three forms based on when bleeding begins: early, classic and late.
All three result from insufficient vitamin K in the baby's body. The condition was historically known as hemorrhagic disease of the newborn.
Early VKDB
Early VKDB develops within the first 24 hours after birth.
It is primarily associated with medications taken by the mother during pregnancy rather than events occurring after delivery.
These medications include warfarin, a blood thinner; certain anticonvulsants used to control seizures; and some drugs prescribed to treat tuberculosis.
Such medications can interfere with the body's ability to use vitamin K, and their effects may reach the baby before birth.
Early VKDB can begin shortly after delivery, sometimes before or around the time a routine vitamin K injection would be administered.
A mother's medication history is therefore an important part of assessing the risk.
Classic VKDB
Classic VKDB generally appears during the first week of life.
It is associated with the naturally low vitamin K reserves newborns have during their first days, before those reserves have had time to increase.
Late VKDB
Late VKDB develops from approximately two weeks to six months after birth.
It occurs most frequently in babies who are exclusively breastfed and did not receive the vitamin K injection.
By this stage, most infants have already left the hospital, making the condition particularly concerning for families.
Bleeding inside the brain is one of the most serious complications of VKDB. Because the hemorrhage occurs inside the skull, it may not be visible from the outside. Pressure on brain tissue can lead to permanent damage.
The timing of bleeding can help doctors identify potential causes.
Bleeding on the first day of life may point toward medications taken during pregnancy. Bleeding at two months may raise questions about feeding practices and whether the newborn received vitamin K. Classic VKDB falls between these two periods.
Women who took warfarin, anticonvulsants or tuberculosis medications during pregnancy should discuss those medications with their obstetrician and their baby's pediatrician before delivery.
5. Recognizing the Warning Signs of Vitamin K Deficiency Bleeding
Easy bruising, bleeding from the nose, gums or umbilical stump, and blood in a baby's stool can all signal vitamin K deficiency bleeding.
Infants with liver or bile duct disease, as well as those with conditions that interfere with fat absorption, face a higher risk.
Late VKDB can emerge between approximately two weeks and six months of age, often after families have left the hospital. The first signs may appear at home, far from the immediate medical supervision available in a newborn nursery.
Some warning signs are subtle.
A bruise may appear without an obvious injury. Blood may seep from the umbilical stump or gums. A diaper may contain bright red blood or dark, tarry stool.
Other symptoms can be more difficult to recognize.
Jaundice, which causes yellowing of the skin or the whites of the eyes, can signal an underlying liver problem when it persists beyond approximately two weeks.
Vomiting, unusual sleepiness, lethargy or seizures may indicate bleeding inside the skull. Such bleeding is among the most dangerous complications associated with VKDB.
In some infants, there are no preceding warning signs. An intracranial hemorrhage may be the first indication that something is seriously wrong.
Which Babies Face a Higher Risk?
Certain medical conditions can make vitamin K deficiency more likely.
Biliary atresia, for example, is a condition in which the bile ducts are blocked or absent. This prevents bile from reaching the intestine.
Bile is essential for absorbing fat-soluble vitamins, including vitamin K. Other diseases affecting the liver or bile ducts can disrupt absorption in a similar way.
Malabsorption disorders also increase the risk.
In cystic fibrosis, thick mucus can prevent the pancreas from releasing the enzymes needed to digest fat properly. When fat absorption declines, vitamin K absorption can decline as well.
Unexplained bleeding, prolonged jaundice, seizures or sudden lethargy in a young infant require prompt medical attention.
A pediatrician can order blood-clotting tests and determine whether treatment is necessary.
6. The Recommended Vitamin K Dose for Newborns
The American Academy of Pediatrics recommends that every newborn receive a single intramuscular dose of vitamin K within six hours of birth.
For full-term infants, the standard dose is 0.5 to 1 milligram, administered into the thigh muscle.
The six-hour window provides some flexibility for delivery teams. The injection does not have to be given immediately after birth.
It can be scheduled around the newborn's first examination, initial feeding or early skin-to-skin contact, provided it is administered within the recommended period.
Parents who want uninterrupted time with their newborn before the injection can discuss the timing with their care team.
A Single Dose Is Usually Enough
The vitamin K injection is designed as a one-time preventive measure.
A baby who receives the recommended intramuscular dose at birth does not need a series of follow-up injections to complete the standard prophylaxis.
That single-dose approach is one of the main practical advantages of the injection compared with alternative methods of administering vitamin K.
Premature infants require a different approach.
Smaller preterm babies receive a dose adjusted to their body weight rather than automatically receiving the standard amount used for full-term newborns.
The neonatal team determines the appropriate dose for each infant. Parents of premature babies can ask their medical team how much vitamin K their child received.
7. Why the Injection Goes Into the Thigh
The location of the injection is important.
Vitamin K1 is administered into the vastus lateralis, the muscle located on the outer front portion of the thigh.
Newborns have more developed muscle mass in this area than in their upper arms, making the thigh the preferred location for many infant injections.
The procedure is brief and is generally performed by a nurse in the delivery room or nursery.
How the Muscle Provides a Gradual Supply
Injecting vitamin K into muscle tissue rather than directly into a vein changes how the body absorbs the nutrient.
The muscle acts as a depot, holding the vitamin and gradually releasing it into the bloodstream.
This slow-release process allows a single injection to support a newborn over the following weeks, while the baby's natural vitamin K intake remains limited.
The procedure itself is usually completed in a matter of seconds.
8. Why Oral Vitamin K Is Not the Standard in the United States
No oral vitamin K product is approved by the U.S. Food and Drug Administration for preventing bleeding in newborns.
Instead, U.S. hospitals administer newborn vitamin K prophylaxis through an injection.
The approved option is injectable vitamin K1, known by its generic name phytonadione.
A single intramuscular dose provides the preventive amount at once, without requiring additional doses to complete the standard regimen.
Oral vitamin K programs used in some other countries operate differently, often requiring several doses over a period of weeks.
That schedule introduces the possibility of missed or delayed doses.
Each administration depends on a parent or health care provider remembering to give the medication on time. A forgotten dose can leave a baby with less protection during a period when vitamin K reserves remain particularly low.
The responsibility shifts from a health care professional administering the injection at birth to a family managing a newborn's care at home.
Absorption Creates Another Challenge
Vitamin K is fat-soluble, meaning the digestive system requires bile to absorb it effectively.
An infant who spits up or vomits shortly after an oral dose may not retain the full amount.
Babies with undiagnosed problems affecting bile flow may also absorb very little of the vitamin they swallow.
This is particularly concerning because some of these infants already face an elevated risk of bleeding.
The intramuscular injection avoids the digestive tract entirely.
These limitations are especially important when considering late vitamin K deficiency bleeding, which can emerge between approximately two weeks and six months of age.
Oral vitamin K regimens provide less reliable protection against late VKDB than the single intramuscular injection.
Parents considering oral drops instead of the injection can discuss their concerns with a pediatrician before delivery.
Choosing an oral route still means choosing vitamin K. It changes how the nutrient is administered and how many doses are needed, but it does not eliminate the newborn's need for the vitamin.

Discussion
No comments yet. Be the first to join the discussion!
FOLLOW US

Recent Posts






Don’t Miss It

Jenson Huang Scandal: Nvidia Investigates CEO’s…
SAN FRANCISCO (AP) — Jenson Huang, the chief executive of…
By – Jackie Allen
Dr. Trump Found Nothing New In…
Decades before the modern UFO era, Nikola Tesla believed he…
By – Samuel Lopez
Trump Downplays Iran Strikes as U.S.…
WASHINGTON — President Donald Trump says major new Iran strikes…
By – Michallie K Harrison
Russell Brand Sentenced to 10½ Years…
LONDON — Russell Brand was sentenced to 10 years and…
By – Michallie K Harrison
Nvidia Probes Alleged Spy Operation Targeting…
WASHINGTON — Nvidia’s Jensen Huang investigation will examine reports that…
By – Michallie K Harrison
Chappelle’s Charlie Kirk Joke Tests Free…
Dave Chappelle’s Charlie Kirk joke has drawn angry responses from…
By – Michallie K Harrison
Popular Vote Compact Nears 270 Electoral…
Democratic wins in key state governments have supporters of the…
By – Derek Johnson
Former NYPD Employee Charged in Brooklyn…
Sayed Mohassib, a former NYPD employee, is charged with second-degree…
By – Derek Johnson
JWST discovers 104 magnified stellar events…
Astronomers using NASA’s James Webb Space Telescope have identified 104…
By – Jackie Allen
Artemis Program: NASA Seeks New Astronauts…
CAPE CANAVERAL, Fla. — NASA is recruiting a new generation…
By – Jackie Allen
Dana White Reportedly Declines Trump White…
By Samuel Lopez – USA Herald | November 8, 2026…
By – Samuel Lopez
Iran Rejects US Reply on Hormuz…
Iran calls Washington’s reply on reopening the Strait of Hormuz…
By – Derek Johnson
Alaska Senate Election Erupts Into Legal…
Three Critical Issues Behind Alaska’s Ballot Dispute Democrat Mary Peltola…
By – Samuel Lopez
Pakistani Astronaut Set to Make History…
BEIJING, Nov. 7, 2026 — A Pakistani astronaut is set…
By – Jackie Allen
New Study Finds Heat Waves of…
The devastating heat waves experienced around the world in recent…
By – Jackie Allen
Stephen Miller to Replace Susie Wiles…
WASHINGTON — President Donald Trump announced Friday that Stephen Miller,…
By – Jackie Allen
Binance $6.3 Billion Heist Puts Crypto…
The record-breaking Binance $6.3 Billion Heist is sending shockwaves through…
By – Tyler Brooks
Anthem $160M Autism Therapy Scheme: Elevance…
Elevance Health and its Anthem-affiliated companies are seeking at least…
By – Tyler Brooks
Justice Sotomayor Calls For Supreme Court…
By Samuel López | USA Herald November 7, 2026 Presidential…
By – Samuel Lopez
Yella Beezy’s $40,000 Murder-For-Hire Trial Takes…
Inside the Murder-for-Hire Case Prosecutors allege Yella Beezy paid $40,000…
By – Samuel Lopez
Can Elephants Sue For Freedom? Hawaii…
What’s at Stake for Mari and Vaigai A legal first…
By – Samuel Lopez
On Monday Supreme Court Weighs Whether…
What’s at Stake for Federal Prisoners A prisoner’s broken tailbone…
By – Samuel Lopez
KPMG Settles – Agrees To Pay…
What the $224.5 Million Settlement Reveals KPMG agreed to a…
By – Samuel Lopez
Mike Tyson And Ric Flair Score…
Inside the $50 Million Legal Battle A federal judge rejected…
By – Samuel Lopez
Online Fashion Retailer Revolve Group, Inc.…
What Court Records Reveal About the Revolve Lawsuit A federal…
By – Samuel Lopez
Four States Sue Trump Administration Over…
What’s at Stake in the Medicaid Court Battle Four states…
By – Samuel Lopez
McDonald’s Sued Over ‘Sugar-Free’ Coffee Drinks…
What’s Brewing Behind the Lawsuit Eight McCafé beverages allegedly contain…
By – Samuel Lopez
American Family Insurance Faces New Federal…
Developments Worth Watching in the Insurance Lawsuit Stacy Penning filed…
By – Samuel Lopez
Better Home & Finance Faces Expanded…
NEW YORK — Better Home & Finance Holding Company (NASDAQ: BETR)…
By – Samuel Lopez
Costco Hit With Federal Class Action…
Behind the Price Tags 1. Costco faces allegations that its advertised…
By – Samuel Lopez
Hackers Target French Blood Banks In…
By Samuel Lopez – USA Herald A cyberattack targeting blood-storage…
By – Samuel Lopez
AI Flagged Bias in Trump Climate…
WASHINGTON — Researchers on a Trump climate panel asked Microsoft…
By – Michallie K Harrison
Russell Brand Convicted of Rape, Taken…
LONDON — Russell Brand was convicted of rape and three…
By – Michallie K Harrison
Supreme Court Takes Up Colorado Preschool…
What the Justices Must Decide Colorado says every publicly funded…
By – Samuel Lopez
California Botox Doctor Gets 15 Years…
What the Medicare Records Revealed A California doctor billed more…
By – Samuel Lopez
A New 2026 Twin Study Revives…
Three Takeaways Identical twins and triplets were separated through adoption…
By – Samuel Lopez
Dallas Cowboys Face Crisis After Crushing…
By Jackie Allen | USA Herald The Dallas Cowboys are…
By – Jackie Allen
WNBA: DeWanna Bonner Makes Emotional Admission…
ATLANTA — The WNBA Finals ended in heartbreak for the…
By – Jackie Allen
Inés Gómez Mont Arrested by ICE…
MIAMI — Inés Gómez Mont, a former television personality who…
By – Jackie Allen
Bill Belichick and Jordon Hudson Reportedly End…
Bill Belichick and Jordon Hudson reportedly ended their romantic relationship…
By – Jackie Allen
Brewers Beat Rays to Win First…
ST. PETERSBURG, Fla. — The Milwaukee Brewers won their first…
By – Michallie K Harrison
Connor Hellebuyck Traded to New Jersey…
The New Jersey Devils have made a major move to…
By – Tyler BrooksNo posts found.
No posts found.


Join the Discussion
Share your thoughts, ask questions, and engage with
other readers. Sign in or create a free account to
comment.